Why Kidney Screening Can Matter Before Symptoms Begin
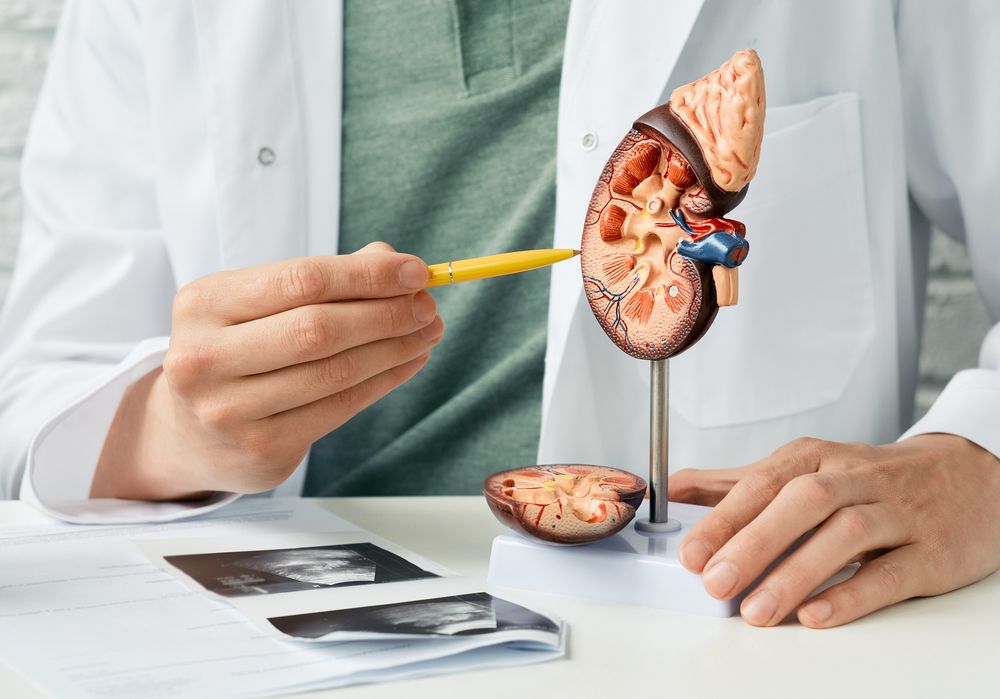
Kidney disease often develops quietly. A person may feel well even while laboratory testing begins to show changes in filtration or protein in the urine. The kidneys are patient organs. They can lose a meaningful percentage of their filtering capacity while a person continues feeling completely normal, going about daily life with no hint that anything has changed. That silence is precisely what makes kidney disease tricky to catch early and exactly why screening exists as a category separate from waiting for symptoms to show up.
Not everyone needs the same level of kidney monitoring. The people who benefit most tend to share specific risk factors: diabetes, high blood pressure, cardiovascular disease, or a family history of kidney failure, along with anyone whose routine bloodwork has already turned up something unexpected, elevated creatinine, protein in the urine, or another abnormal marker worth a second look. Nephrology Associates of Northern Illinois and Indiana (NANI) runs its Bergen Kidney Center out of offices in Englewood and Westwood, NJ, where patients carrying these risk factors can get a clearer read on kidney health well before any noticeable symptom would have prompted the question on its own.
Who May Benefit From Kidney Disease Screening?
Kidney screening is generally most useful when a person has factors that increase the likelihood of chronic kidney disease rather than as a universal test for everyone.
Diabetes and high blood pressure are two of the most common causes of chronic kidney disease in adults. Over time, both conditions can damage the small blood vessels and filtering structures inside the kidneys.
Heart and vascular disease can also be associated with kidney problems because the kidneys depend on healthy circulation. A family history of kidney failure may raise concern for inherited conditions or shared risk factors.
Other circumstances may prompt testing as well, particularly when previous laboratory work has shown elevated creatinine, protein in the urine, blood in the urine, or other unexplained abnormalities.
Understanding kidney protection can help patients see why screening is often paired with management of blood pressure, diabetes, medications, and other risks that can influence long-term kidney health.
What Tests Are Commonly Used?
Kidney screening usually involves both blood and urine testing. These tests provide different but complementary information.
Common screening measurements may include:
- Serum creatinine, which is used to estimate kidney filtration
- Estimated glomerular filtration rate, or eGFR
- Urine albumin-to-creatinine ratio, or UACR
- Urinalysis to look for protein, blood, or other abnormalities
- Blood pressure measurement
- Additional blood tests when electrolyte or metabolic concerns are present
No single result tells the entire story. Clinicians generally interpret these measurements together and compare them with previous results when available.
Understanding eGFR
The estimated glomerular filtration rate is one of the most commonly used measures of kidney function. It is calculated from a blood creatinine measurement along with other patient information.
An eGFR can help estimate how efficiently the kidneys are filtering the blood. However, one reduced value does not automatically establish chronic kidney disease. Temporary illness, dehydration, medication effects, and other factors may influence kidney measurements.
Chronic kidney disease generally involves kidney abnormalities that persist for at least three months. Repeat testing can therefore be important when an unexpected result appears.
Learning more about kidney function can make it easier to understand why clinicians often focus on trends in eGFR rather than one isolated number.
Why Urine Albumin Testing Is Important
Blood testing alone can miss some early kidney damage. A person may have an eGFR that remains relatively preserved while abnormal amounts of albumin are already passing into the urine.
Albumin is a protein that normally remains in the bloodstream. When the kidney’s filtering structures are damaged, some albumin may leak into the urine.
The urine albumin-to-creatinine ratio, or UACR, is commonly used to measure this leakage. A result above the expected range may indicate kidney damage, particularly when it persists on repeat testing.
Albuminuria is especially important in people with diabetes or hypertension because it can appear before more substantial loss of filtration develops.
Why Abnormal Results May Need to Be Repeated
A single abnormal test does not always mean permanent kidney disease is present.
Urine protein may temporarily increase during fever, infection, dehydration, intense exercise, or another acute illness. Creatinine and eGFR can also shift during periods of dehydration or medication changes.
For this reason, clinicians may repeat testing after a temporary problem has resolved. The goal is to determine whether the abnormality persists and whether a clear pattern is developing.
Repeated results may also help show whether kidney function is stable, worsening, or improving after treatment changes.
This emphasis on trends is one reason patients should keep copies of previous laboratory results when possible, especially when seeing a nephrologist for the first time.
How Diabetes Raises Kidney Risk
High blood glucose can gradually damage the kidney’s filtering structures. This process may lead to albumin in the urine and, over time, reduced kidney filtration.
Because early diabetic kidney disease may not cause symptoms, routine kidney testing is an important part of diabetes care. Urine albumin and eGFR provide different information and are often assessed together.
The presence of diabetes does not mean kidney disease is inevitable. Blood sugar management, blood pressure treatment, appropriate medications, and regular testing can all influence risk.
When abnormal kidney findings do appear, further evaluation can help determine whether diabetes is the likely cause or whether another kidney condition should also be considered.
High Blood Pressure and Kidney Health
The relationship between hypertension and kidney disease works in both directions.
High blood pressure can damage the small blood vessels within the kidneys. At the same time, damaged kidneys may have more difficulty regulating sodium, fluid, and hormones that influence blood pressure.
Patients whose blood pressure remains difficult to control despite treatment may need kidney testing as part of the evaluation. Protein in the urine or declining eGFR can provide additional evidence that the kidneys are being affected.
Blood pressure control is therefore an important part of reducing kidney risk even before chronic kidney disease has been diagnosed.
What Happens If Screening Finds a Problem?
An abnormal screening result is usually the beginning of an evaluation rather than a final diagnosis.
A clinician may review medical history, medications, blood pressure, diabetes control, previous laboratory trends, and family history. Repeat blood and urine testing may be ordered to confirm the findings.
Depending on the results, further evaluation may include kidney ultrasound, specialized blood tests, urine microscopy, or other studies. Some patients may be referred to a nephrologist when kidney function is declining, proteinuria is substantial, or the cause of the abnormality is uncertain.
Understanding kidney disease in this broader context can help patients recognize that diagnosis depends on the cause, duration, and pattern of abnormalities rather than a single laboratory result.
When Nephrology Follow-Up May Be Appropriate
Primary care clinicians often identify the first signs of a kidney concern. Nephrology referral may become useful when those findings require more specialized evaluation or management.
Examples include persistently reduced eGFR, significant urine protein, blood in the urine, difficult-to-control blood pressure, unexplained electrolyte abnormalities, or a rapid change in kidney function.
Patients may also be referred when the cause of kidney disease is unclear or when treatment decisions become more complex.
The timing of referral varies. Some patients benefit from nephrology involvement early, while others can continue to be monitored by their primary care clinician until more specialized input is needed.
Taking a Proactive Approach in Bergen
Kidney disease screening does not necessarily mean that a serious problem will be found. Its purpose is to identify changes that might otherwise remain unnoticed and determine whether they require monitoring or treatment.
For Bergen County patients with diabetes, hypertension, cardiovascular disease, family history, or abnormal laboratory results, blood and urine testing can provide an important starting point.
NANI’s Bergen Kidney Center serves communities throughout the area through offices in Englewood and Westwood. When screening identifies a kidney concern, nephrology follow-up can help clarify the cause, interpret laboratory trends, and develop a plan for protecting kidney function over time.
Sources
Kidney Disease: Improving Global Outcomes CKD Work Group. (2024). KDIGO clinical practice guideline for the evaluation and management of chronic kidney disease. Kidney International.
Chen, T. K., Knicely, D. H., & Grams, M. E. (2019). Chronic kidney disease diagnosis and management: A review. JAMA.
Levey, A. S., Coresh, J., Tighiouart, H., Greene, T., & Inker, L. A. (2020). Measured and estimated glomerular filtration rate: Current status and future directions. Nature Reviews Nephrology.