When Protein Shows Up in a Urine Test
Protein in the urine, known as proteinuria, can be an important clue about kidney health. Healthy kidneys generally keep important proteins in the bloodstream while filtering waste and excess fluid into the urine. When the kidney’s filtering structures are damaged or under stress, more protein may pass through.
Proteinuria does not always mean someone has advanced kidney disease. In some cases, it may be temporary. In others, persistent protein loss can be an early sign of chronic kidney disease even when a person feels well and kidney filtration appears relatively preserved.
Nephrology Associates of Northern Illinois and Indiana (NANI) evaluates kidney-related laboratory changes for patients in Berwyn and North Chicago, Illinois, and Bergen, New Jersey. Understanding why protein appears in the urine and how it is measured can make follow-up testing easier to interpret.
Why the Kidneys Normally Keep Protein in the Blood
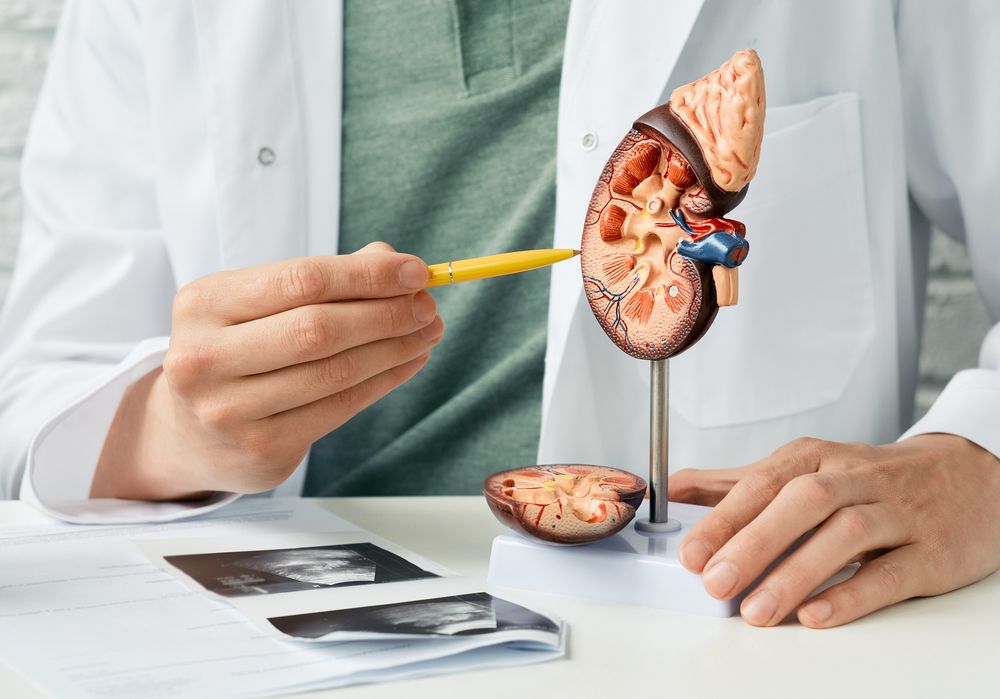
Each kidney contains tiny filtering units called glomeruli. These structures remove waste products and excess water while helping retain blood cells and proteins the body needs.
Albumin is one of the most important proteins found in blood. Under normal conditions, very little albumin passes into the urine. When the filtration barrier becomes damaged, albumin and sometimes other proteins can leak through.
This is why urine protein testing provides information that a blood creatinine test alone cannot. A person may have an estimated glomerular filtration rate, or eGFR, that remains relatively preserved while albumin is already appearing in the urine.
Learning how kidney function is measured helps explain why blood and urine tests are often interpreted together rather than relying on a single laboratory value.
Proteinuria and Albuminuria Are Closely Related
The terms proteinuria and albuminuria are sometimes used interchangeably, but they are not the same.
Proteinuria means that an abnormal amount of protein is present in the urine. Albuminuria refers specifically to albumin. Because albumin is commonly associated with damage to the kidney’s filters, clinicians frequently measure it when screening for or monitoring kidney disease.
One commonly used test is the urine albumin-to-creatinine ratio, or UACR. This compares the amount of albumin with creatinine in a urine sample and helps account for differences in how concentrated the urine is.
A UACR above 30 mg/g is generally considered abnormal. However, the significance of any result depends on whether it persists, the patient’s kidney function, and other medical conditions.
Why Repeat Testing May Be Necessary
One abnormal urine test does not always establish chronic kidney disease. Protein levels may increase temporarily because of circumstances that place short-term stress on the body or kidneys.
Possible reasons for temporary proteinuria include:
- Dehydration
- Fever or infection
- Intense exercise
- Acute illness
- A flare of heart failure
- Other short-term physical stress
Because these factors can affect the result, a clinician may recommend repeating the urine test after the temporary issue has resolved.
Persistent proteinuria is more concerning because it may represent ongoing kidney damage. Chronic kidney disease is generally defined by kidney abnormalities that remain present for at least three months, so trends over time are important.
Conditions Associated With Persistent Proteinuria
Diabetes and high blood pressure are among the most common conditions associated with chronic kidney damage and albumin in the urine. Over time, both can injure the small blood vessels and filtering structures inside the kidneys.
Proteinuria may also occur with glomerular diseases, autoimmune conditions, inherited kidney disorders, cardiovascular disease, and other illnesses that affect kidney structure or circulation.
Sometimes urine protein is the first abnormality that leads to further evaluation. A patient may not have swelling, fatigue, changes in urination, or other noticeable symptoms.
Understanding the broader picture of kidney disease can help patients see why proteinuria is considered alongside blood pressure, diabetes history, eGFR, family history, and other laboratory findings.
Symptoms May Not Appear Early
Mild or moderate proteinuria often causes no obvious symptoms. This is one reason urine testing can be valuable for people who have risk factors for kidney disease.
When protein loss becomes more significant, some patients may notice unusually foamy urine. Persistent foaming can occur when higher amounts of protein change the surface properties of urine, although foam alone cannot diagnose a kidney condition.
More substantial protein loss may also contribute to swelling in the ankles, legs, face, or around the eyes. This can happen when blood albumin falls and fluid shifts into surrounding tissues.
Symptoms should be evaluated in context. Foamy urine and swelling can have causes unrelated to kidney disease, and laboratory testing is needed to determine whether proteinuria is present.
How Proteinuria Is Evaluated
Evaluation usually begins with urine testing and a review of kidney function. A dipstick may detect protein, while UACR provides a more specific measurement of urine albumin.
Blood tests commonly include creatinine and eGFR. The clinician may also evaluate electrolytes, blood glucose, albumin, and other measurements depending on the situation.
Medical history matters as well. Questions may focus on diabetes, blood pressure, heart disease, autoimmune conditions, family history of kidney disease, recent infections, medications, or supplements.
When protein levels are unusually high or the cause is uncertain, additional evaluation may include urine microscopy, imaging, specialized blood tests, genetic testing, or kidney biopsy.
Not every patient needs the same testing. The amount of protein, changes in eGFR, symptoms, age, and suspected underlying cause all influence the workup.
Why the Amount of Protein Matters
Proteinuria exists along a spectrum. Small but persistent amounts of albumin may signal early kidney injury, while larger amounts can indicate more substantial damage to the filtration barrier.
The degree of albuminuria also helps clinicians estimate the risk of chronic kidney disease progression. In general, higher or increasing urine albumin is associated with greater kidney and cardiovascular risk.
For this reason, monitoring is not simply about determining whether protein is present. Clinicians may compare UACR results over time to see whether the level is stable, rising, or responding to treatment.
A reduction in urine albumin can be a positive sign, particularly when it occurs alongside stable kidney filtration and improved blood pressure or diabetes control.
Managing the Conditions Behind Proteinuria
Treatment usually focuses on the underlying cause rather than proteinuria as an isolated laboratory finding.
For patients with high blood pressure, treatment may include medications that help lower pressure within the kidney’s filtering structures. Diabetes management can also be important because prolonged high blood sugar can contribute to glomerular damage.
Nutrition, sodium intake, physical activity, smoking status, weight management, and medication use may all influence kidney risk. Some over-the-counter pain relievers can also place additional stress on kidney function in susceptible patients.
Following individualized kidney protection strategies can help address several of these risk factors together while laboratory results are monitored over time.
When Nephrology Evaluation May Be Recommended
Not every abnormal urine result requires specialist care, but nephrology referral may be appropriate when proteinuria is persistent, substantial, increasing, or accompanied by other kidney abnormalities.
Additional reasons for referral may include declining eGFR, blood in the urine, difficult-to-control blood pressure, unexplained swelling, abnormal electrolyte levels, or uncertainty about the underlying diagnosis.
The nephrologist may help determine whether the proteinuria is related to diabetes or hypertension, a glomerular disorder, medication effects, inherited disease, or another condition.
Early evaluation can be particularly useful when the cause is unclear or when laboratory values are changing quickly.
Looking at Proteinuria as Part of the Bigger Picture
Protein in the urine is not a diagnosis by itself. It is a finding that needs to be interpreted alongside kidney filtration, medical history, blood pressure, diabetes status, symptoms, and repeated testing.
A temporary increase may resolve, while persistent proteinuria may provide an early warning of kidney damage before noticeable symptoms appear. Tracking the amount over time can also help clinicians assess whether kidney disease is stable or changing.
Across NANI’s practices in Berwyn and North Chicago, Illinois, and Bergen, New Jersey, nephrology care includes evaluating laboratory findings such as proteinuria in the context of overall kidney health. Understanding what the test means can help patients follow their results more confidently and recognize why continued monitoring may be recommended.
Sources
Kidney Disease: Improving Global Outcomes CKD Work Group. (2024). KDIGO clinical practice guideline for the evaluation and management of chronic kidney disease. Kidney International.
Chen, T. K., Knicely, D. H., & Grams, M. E. (2019). Chronic kidney disease diagnosis and management: A review. JAMA.
Levey, A. S., Eckardt, K. U., Dorman, N. M., et al. (2020). Nomenclature for kidney function and disease: Executive summary and glossary from a Kidney Disease: Improving Global Outcomes consensus conference. Kidney International.